This caused some consternation among general surgeons on Twitter. I tweeted, “Interesting. Lifestyle is finally catching up to us. I think it will get worse.”

"Man is least himself when he talks in his own person. Give him a mask, and he will tell you the truth." Oscar Wilde
Showing posts with label general surgery. Show all posts
Showing posts with label general surgery. Show all posts
Wednesday, September 19, 2018
“Number of medical students pursuing surgery specialty drops by half”
This caused some consternation among general surgeons on Twitter. I tweeted, “Interesting. Lifestyle is finally catching up to us. I think it will get worse.”


Monday, January 8, 2018
Is chronic pain after inguinal hernia repair a big problem?
Yesterday one of my twitter followers posted this:
 He was referring to a paper in the British Journal of Surgery that said 15.2% of patients who had inguinal herniorrhaphies complained of severe chronic pain one year after the surgery. Open hernia repairs caused significantly more chronic pain than did endoscopic total extraperitoneal [TEP] repairs, but the reoperation rate was significantly higher for TEP procedures.
The study included almost 23,000 patients and was based on data from the Swedish Hernia Registry and a questionnaire sent to the patients one year after their initial hernia operation. Pain was rated on a scale of 1 to 7 and was considered chronic if it was present for more than 3 months and interfered with daily activities.
The recurrence rate for the 18,000 patients who had open anterior mesh repair was 3.4% compared to 23.3% for the 2688 who had TEP repairs.
The authors concluded that the trade-off for less pain was an increased recurrence rate. Only 232 [1.39%] of the 1666 patients with recurrent hernias had undergone repeat herniorrhaphy.
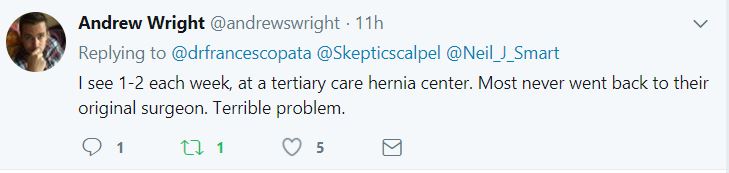
Some of the comments on Twitter were as follows:


When I was in private practice in the early 1980s, I invited all of my post-op hernia patients to return to my office for yearly follow-up at no charge.
One day, a nice elderly gentleman was sitting in the exam room when I walked in. After an exchange of pleasantries, I asked him how his hernia repair was doing. He said he had no problems and was quite happy.
I had him stand up and when he lifted his gown, I saw a softball-sized recurrent hernia. Ever since then, I have not trusted any studies in which follow-up was not done in person.
Based on my experience, the recurrence rate after groin hernia repairs could even be higher than the Swedish study reported.
The incidence of chronic pain after inguinal herniorrhaphy may depend on how surgeons follow their patients.

The study included almost 23,000 patients and was based on data from the Swedish Hernia Registry and a questionnaire sent to the patients one year after their initial hernia operation. Pain was rated on a scale of 1 to 7 and was considered chronic if it was present for more than 3 months and interfered with daily activities.
The recurrence rate for the 18,000 patients who had open anterior mesh repair was 3.4% compared to 23.3% for the 2688 who had TEP repairs.
The authors concluded that the trade-off for less pain was an increased recurrence rate. Only 232 [1.39%] of the 1666 patients with recurrent hernias had undergone repeat herniorrhaphy.
Some of the comments on Twitter were as follows:


One day, a nice elderly gentleman was sitting in the exam room when I walked in. After an exchange of pleasantries, I asked him how his hernia repair was doing. He said he had no problems and was quite happy.
I had him stand up and when he lifted his gown, I saw a softball-sized recurrent hernia. Ever since then, I have not trusted any studies in which follow-up was not done in person.
Based on my experience, the recurrence rate after groin hernia repairs could even be higher than the Swedish study reported.
The incidence of chronic pain after inguinal herniorrhaphy may depend on how surgeons follow their patients.
Friday, November 17, 2017
Residents, duty hours, and respect
The following is an email I received.
Fossil: "In my day we worked __ many hours and operated all night and never slept or ate and were glad of it. It made me the surgeon I am today. You will never have this privilege."
Me: "Wow, I agree. You had it much harder." Meanwhile, I am thinking:
Monday, November 13, 2017
Useless general surgical interventions that should no longer be done
England’s National Health Service (NHS) could save €153 million [$178 million USD] per year by scrapping 71 low-value general surgery practices says a recently published paper in the British Journal of Surgery.
The authors, from Imperial College London, extensively reviewed the literature and Choosing Wisely recommendations from a number of countries.
I agree with many of the 71 including performing a cholecystectomy during the first admission for a patient with symptomatic gallstones instead of waiting for another admission (saving more than €54 million) and not repairing minimally symptomatic inguinal hernias, which they estimate would save over €32 million.
The Telegraph reported, “The team also discovered that robotic surgery has ‘little or no advantage’ when compared with traditional keyhole operations and said it must be ‘considered a candidate for disinvestment.’” This probably wouldn’t fly here in the US, because—like guns—too many robots are already in the hands of users.
The authors, from Imperial College London, extensively reviewed the literature and Choosing Wisely recommendations from a number of countries.
I agree with many of the 71 including performing a cholecystectomy during the first admission for a patient with symptomatic gallstones instead of waiting for another admission (saving more than €54 million) and not repairing minimally symptomatic inguinal hernias, which they estimate would save over €32 million.
The Telegraph reported, “The team also discovered that robotic surgery has ‘little or no advantage’ when compared with traditional keyhole operations and said it must be ‘considered a candidate for disinvestment.’” This probably wouldn’t fly here in the US, because—like guns—too many robots are already in the hands of users.
Tuesday, June 20, 2017
Some general surgery residency graduates may not be competent to operate
A new study says 84% of general surgery residents in their last six months of training were rated as competent to perform the five most common general surgery core procedures—appendectomy, cholecystectomy, ventral hernia repair, groin hernia repair, and partial colectomy. However the percentage of those judged competent varied from a high of 96% for appendectomy to a low of 71% for partial colectomy.
When analyzing the other 127 core operations of general surgery, the investigators found that 26% of residents in their last six months of training were felt to not be competent to perform at least some of those procedures.
The study was presented at the annual meeting of the American Surgical Association in April 2017 and reported in ACS Surgery News.
Data were compiled from ratings of 522 residents by 437 faculty yielding 8526 different observations.
For all of the procedures rated, maximum resident autonomy was observed for 33% of cases, and the more complex the case, the less ready the residents were to perform it on their own.
The lead author of the study, Dr. Brian George of the University of Michigan, was asked whether the duration of surgery training should be increased. He answered, “The 20,000 hours of surgical residency should be enough to train a general surgeon to competence—it's up to us to figure out how.”
When analyzing the other 127 core operations of general surgery, the investigators found that 26% of residents in their last six months of training were felt to not be competent to perform at least some of those procedures.
The study was presented at the annual meeting of the American Surgical Association in April 2017 and reported in ACS Surgery News.
Data were compiled from ratings of 522 residents by 437 faculty yielding 8526 different observations.
For all of the procedures rated, maximum resident autonomy was observed for 33% of cases, and the more complex the case, the less ready the residents were to perform it on their own.
The lead author of the study, Dr. Brian George of the University of Michigan, was asked whether the duration of surgery training should be increased. He answered, “The 20,000 hours of surgical residency should be enough to train a general surgeon to competence—it's up to us to figure out how.”
Friday, April 21, 2017
Resources 3rd-year medical students study during general surgery clerkships
At the University of Florida medical school, the answers to that question varied widely. According to a paper published ahead of print in the American Journal of Surgery, students at UF use review books, e-books such as UpToDate, government agency and professional organization websites, textbooks, journals, and more.
The recommended textbook for the course is Lawrence’s Essentials of General Surgery, now in its fifth edition.
The authors surveyed the 133 members of the 2014-2015 third-year class, and 92 (69.2%) responded. Regarding each resource used, they could answer with one of four choices: always, usually, sometimes, never.
The recommended textbook for the course is Lawrence’s Essentials of General Surgery, now in its fifth edition.
The authors surveyed the 133 members of the 2014-2015 third-year class, and 92 (69.2%) responded. Regarding each resource used, they could answer with one of four choices: always, usually, sometimes, never.
Friday, February 17, 2017
Will robots eliminate the need for surgeons?
A medical student from Germany emailed me saying he had always wanted to be a surgeon, but someone told him that by 2030 surgeons would no longer be needed because robots would be doing all the operations. He worried that after years of studying and hard work, he might lose his job to “R2-D2.”
He mentioned IBM’s Watson and a recent paper that appeared in the journal Science Translational Medicine about a robot that can handle and suture bowel.
He asks, “What do you think about the future of surgery?”
Thank you for your email and the link to the paper.
I read the paper and was amused by its title "Supervised autonomous robotic soft-tissue surgery" which is an oxymoron. The definition of autonomous is "acting independently or having the freedom to do so." This “supervised” robot is not really autonomous.
The robot is capable of performing a nearly technically perfect intestinal anastomosis but still needs a human surgeon to open the abdomen, prepare the bowel for the procedure, tidy up, and close. I'm not sure that this is any different than when surgical staplers were introduced. This robot is simply making the operation easier and possibly more precise.
Surgeons will still be needed in case the robot makes a mistake like causing bleeding while placing a suture near the mesentery. If bleeding in that area is not promptly controlled, a large hematoma can develop and possibly compromise the blood supply to the anastomosis. And will the robot be able to decide who needs an operation and when to do it?
One worrisome byproduct of surgical stapling is that many graduates of residency programs within the last 15 or 20 years have little experience in performing a hand sewn bowel anastomosis. What will they do if the hospital runs out of staplers? Soon, I guess they could consult the (somewhat) autonomous robot.
I have written about automation and the erosion of surgical skills. This problem also affects pilots. I have also addressed the concept of robots operating alone. I don't see it happening any time soon.
I think there will always be a need for surgeons. Even the smartest robot is going to have some trouble dealing with a trauma patient who is hypotensive.
The future will take care of itself. In the 1980s, people were concerned about the demise of general surgery. Opinion pieces with titles like “Will the general surgeon become extinct?” and “Is general surgery a dying specialty?” appeared in major journals like JAMA and the World Journal of Surgery.
Then in 1990, laparoscopic cholecystectomy opened the door to a whole new area of general surgery that no one had ever dreamed of.
Good luck with your studies and your surgical career.
He mentioned IBM’s Watson and a recent paper that appeared in the journal Science Translational Medicine about a robot that can handle and suture bowel.
He asks, “What do you think about the future of surgery?”
Thank you for your email and the link to the paper.
I read the paper and was amused by its title "Supervised autonomous robotic soft-tissue surgery" which is an oxymoron. The definition of autonomous is "acting independently or having the freedom to do so." This “supervised” robot is not really autonomous.
The robot is capable of performing a nearly technically perfect intestinal anastomosis but still needs a human surgeon to open the abdomen, prepare the bowel for the procedure, tidy up, and close. I'm not sure that this is any different than when surgical staplers were introduced. This robot is simply making the operation easier and possibly more precise.
Surgeons will still be needed in case the robot makes a mistake like causing bleeding while placing a suture near the mesentery. If bleeding in that area is not promptly controlled, a large hematoma can develop and possibly compromise the blood supply to the anastomosis. And will the robot be able to decide who needs an operation and when to do it?
One worrisome byproduct of surgical stapling is that many graduates of residency programs within the last 15 or 20 years have little experience in performing a hand sewn bowel anastomosis. What will they do if the hospital runs out of staplers? Soon, I guess they could consult the (somewhat) autonomous robot.
I have written about automation and the erosion of surgical skills. This problem also affects pilots. I have also addressed the concept of robots operating alone. I don't see it happening any time soon.
I think there will always be a need for surgeons. Even the smartest robot is going to have some trouble dealing with a trauma patient who is hypotensive.
The future will take care of itself. In the 1980s, people were concerned about the demise of general surgery. Opinion pieces with titles like “Will the general surgeon become extinct?” and “Is general surgery a dying specialty?” appeared in major journals like JAMA and the World Journal of Surgery.
Then in 1990, laparoscopic cholecystectomy opened the door to a whole new area of general surgery that no one had ever dreamed of.
Good luck with your studies and your surgical career.
Thursday, September 22, 2016
How long is too long for robotic surgery?
A surgical chairman writes [some details were changed to obscure the surgeon’s identity]:
We currently have surgeons who are trying to establish themselves as experts in performing a certain robotic operation. As an open case, it rarely takes more than about 4-5 hours.
With the robot, it is generally taking around 6 hours as reported in the literature, and morbidity and mortality in expert hands appears to be pretty good.
What is happening in the real world is that surgeons are taking 12 or more hours to perform these operations robotically. I am aware of one death after a 14 hour procedure in another hospital. One case in my own institution took 16 hours, and luckily the patient did well. Of course this sort of data never gets reported publicly.
We currently have surgeons who are trying to establish themselves as experts in performing a certain robotic operation. As an open case, it rarely takes more than about 4-5 hours.
With the robot, it is generally taking around 6 hours as reported in the literature, and morbidity and mortality in expert hands appears to be pretty good.
What is happening in the real world is that surgeons are taking 12 or more hours to perform these operations robotically. I am aware of one death after a 14 hour procedure in another hospital. One case in my own institution took 16 hours, and luckily the patient did well. Of course this sort of data never gets reported publicly.
Monday, September 12, 2016
Surgeons are burned out in, of all places, France
More than half of French gastrointestinal surgeons in training are burned out says a paper published ahead of print in the American Journal of Surgery.
Five hundred gastrointestinal surgery trainees were surveyed, and 65.6% responded. Of those responding, 52% had indications of burnout syndrome—emotional exhaustion, depersonalization of relationships, and lack of self-fulfillment at work—on the well-validated Maslach Burnout Inventory.
Other notable findings were 67% had insomnia, and 12% had thoughts of suicide.
On multivariate analysis, the significant factors associated with burnout syndrome included being confronted with aggression from patients, lack of gratitude from senior colleagues, trainees feeling they had too much responsibility, and not participating in extracurricular activities.
Five hundred gastrointestinal surgery trainees were surveyed, and 65.6% responded. Of those responding, 52% had indications of burnout syndrome—emotional exhaustion, depersonalization of relationships, and lack of self-fulfillment at work—on the well-validated Maslach Burnout Inventory.
Other notable findings were 67% had insomnia, and 12% had thoughts of suicide.
On multivariate analysis, the significant factors associated with burnout syndrome included being confronted with aggression from patients, lack of gratitude from senior colleagues, trainees feeling they had too much responsibility, and not participating in extracurricular activities.
Wednesday, January 27, 2016
My response to a misguided opinion piece about surgery
"There is no place for the surgeon myth in modern medicine" says writer Alexis Sobel Fitts in Aeon Magazine.
Having a sister in medical school apparently qualifies Ms. Fitts to critique the specialty of surgery.
She starts with an old joke "An internist can figure out what’s wrong with you, but he can’t fix it. A surgeon has no idea what’s wrong with you, but he’s happy to fix it." If you read it carefully, you should note that it’s not that funny, and it’s wrong on both counts. No surgeon would ever fix something unless she knew why, and internists have these things called pills which can successfully treat a number of diseases.
She goes on, "After all, fixing problems is corporeal, often removed from the more intellectually nimble task of diagnosis." Apparently she is unaware that surgeons often make diagnoses—occasionally even correct ones, and I’ve written before about the misconception that doing an operation doesn’t require thinking [here and here].
"Surgeons are descended from the barber or the butcher," she says. That was hundreds of years ago. Nowadays, surgeons complete four years of medical school just like her sister and all the other doctors.
"Any missteps might incite devastating consequences, as the surgeon navigates around the vagus nerve, which dictates facial response…" I hope her sister didn’t give her that information. The vagus innervates many structures, but the face isn't one of them.
"Before anaesthesia and antibacterials, a patient undergoing surgery could be assured of two things: immense pain and the likelihood of infection and death." That’s actually three things. Of course without surgery, patients experienced immense pain, infections, and death anyway.
"Since the 1950s, laboratory science has increasingly been the origin of medical innovation. Which is why, over the past four decades, merely a 10th of the articles published in The New England Journal of Medicine have covered surgical innovation." Or maybe it's because The New England Journal is a medically, not surgically, oriented journal.
Here’s the winner. "Surgery’s place at the bottom of the medical hierarchy can be attributed to the crude cruelty of early surgical procedures." Other than Ms. Fitts, who has placed surgery at the bottom of the medical hierarchy? It’s certainly not US medical students who make the surgical specialties among the most competitive of all.
In the 2015 resident match, surgical specialties filled their first-year positions with 80% or more US medical school graduates. In fact, orthopedics matched with 94.3% US grads. Compare those numbers to internal medicine and family medicine, which filled their first-year positions with 49% and 44% US graduates, respectively.
Here's what Wikipedia has to say about its Aeon Magazine entry:
This article has multiple issues. Please help improve it or discuss these issues on the talk page.
The neutrality of this article is disputed.
This article contains content that is written like an advertisement.
This article contains weasel words: vague phrasing that often accompanies biased or unverifiable information.
That pretty much describes the Aeon essay about surgeons too.
Having a sister in medical school apparently qualifies Ms. Fitts to critique the specialty of surgery.
She starts with an old joke "An internist can figure out what’s wrong with you, but he can’t fix it. A surgeon has no idea what’s wrong with you, but he’s happy to fix it." If you read it carefully, you should note that it’s not that funny, and it’s wrong on both counts. No surgeon would ever fix something unless she knew why, and internists have these things called pills which can successfully treat a number of diseases.
She goes on, "After all, fixing problems is corporeal, often removed from the more intellectually nimble task of diagnosis." Apparently she is unaware that surgeons often make diagnoses—occasionally even correct ones, and I’ve written before about the misconception that doing an operation doesn’t require thinking [here and here].
"Surgeons are descended from the barber or the butcher," she says. That was hundreds of years ago. Nowadays, surgeons complete four years of medical school just like her sister and all the other doctors.
"Any missteps might incite devastating consequences, as the surgeon navigates around the vagus nerve, which dictates facial response…" I hope her sister didn’t give her that information. The vagus innervates many structures, but the face isn't one of them.
"Before anaesthesia and antibacterials, a patient undergoing surgery could be assured of two things: immense pain and the likelihood of infection and death." That’s actually three things. Of course without surgery, patients experienced immense pain, infections, and death anyway.
"Since the 1950s, laboratory science has increasingly been the origin of medical innovation. Which is why, over the past four decades, merely a 10th of the articles published in The New England Journal of Medicine have covered surgical innovation." Or maybe it's because The New England Journal is a medically, not surgically, oriented journal.
Here’s the winner. "Surgery’s place at the bottom of the medical hierarchy can be attributed to the crude cruelty of early surgical procedures." Other than Ms. Fitts, who has placed surgery at the bottom of the medical hierarchy? It’s certainly not US medical students who make the surgical specialties among the most competitive of all.
In the 2015 resident match, surgical specialties filled their first-year positions with 80% or more US medical school graduates. In fact, orthopedics matched with 94.3% US grads. Compare those numbers to internal medicine and family medicine, which filled their first-year positions with 49% and 44% US graduates, respectively.
Here's what Wikipedia has to say about its Aeon Magazine entry:
This article has multiple issues. Please help improve it or discuss these issues on the talk page.
The neutrality of this article is disputed.
This article contains content that is written like an advertisement.
This article contains weasel words: vague phrasing that often accompanies biased or unverifiable information.
That pretty much describes the Aeon essay about surgeons too.
Friday, January 8, 2016
Should I become a general surgeon?
One of the rewarding things about blogging is receiving many emails from high school, college, and medical students asking about general surgery as a career.
I try to answer every one of their specific questions and direct them to posts that I've written on the subject.
A recent inquiry stimulated me to review all of my posts and put most of the questions about becoming a general surgeon in one place. They are about 500 words each. I hope you enjoy them. Here they are.
Is the solo general surgeon a dying breed?
What is the future of open surgery?
In what specialties can a surgeon be autonomous?
An applicant worries about the future of general surgery
Will automation affect surgeons' skills?
Going to medical school and becoming a surgeon when you are older
A medical student from the UK discovers surgery and has questions
Is it possible to live a full life as a surgeon?
Choosing a medical specialty is difficult
A med student asks, “Is surgery the right careerfor me?”
Which type of surgery residency should I choose?
Medical school and surgery
Choosing a Medical Specialty Is Difficult
I try to answer every one of their specific questions and direct them to posts that I've written on the subject.
A recent inquiry stimulated me to review all of my posts and put most of the questions about becoming a general surgeon in one place. They are about 500 words each. I hope you enjoy them. Here they are.
Is the solo general surgeon a dying breed?
What is the future of open surgery?
In what specialties can a surgeon be autonomous?
An applicant worries about the future of general surgery
Will automation affect surgeons' skills?
Going to medical school and becoming a surgeon when you are older
A medical student from the UK discovers surgery and has questions
Is it possible to live a full life as a surgeon?
Choosing a medical specialty is difficult
A med student asks, “Is surgery the right careerfor me?”
Which type of surgery residency should I choose?
Medical school and surgery
Choosing a Medical Specialty Is Difficult
Sunday, September 27, 2015
Another Caribbean med school graduate needs advice
I did not attend St. George's, Ross, or Saba. I chose my school because it has a premed program which leads to an MD program. My USMLE Scores on Step 1 and Step 2 CK are above 230.
I did not apply for the 2015 match because I did not have my step 2 CK results until November. It would have been too late. I could have rushed my step 2 but I wanted to get a good score and be a solid applicant. Also I would not have been able to complete my surgical electives in time to get letters of recommendation. At some point, I will be doing research at [a very well-known medical school]. I felt that for these reasons this would make me a better applicant the next year.
Since graduating I have been trying to find a medical related job (scribe) but have had no success. I have reached out to many institutions regarding research opportunities but have come up dry. I may be able to secure a volunteer research position by next month. Do you have any suggestions for me? I knew I would hate being out of the medical field for this long but this was my best bet. Does this gap hurt my chances?
I am concerned that despite your excellent USMLE scores, taking a year off from clinical medicine may cause your application to be rejected immediately. I do not know if a 9 week research elective, even at a premier med school, would be enough to offset your lack of clinical experience over the entire year. Acting as a scribe would not be considered clinical experience.
Another issue is what is the record of your school regarding matching graduates into surgical programs? Since you didn’t tell me your school’s name, I cannot give you any insight into that situation. Even if I did know the school’s name, it may not have published its match results.
To answer your specific questions:
How many gen surg programs should I apply to? I was thinking ~100. That seems reasonable. You should be able to gauge your chances better after you see if you receive any offers for interviews from the 100 programs.
During a gen surg interview, should I be open about my backup specialty? I would advise you to say that you would take a preliminary spot in general surgery if you didn’t match in a categorical position. Admitting that you would do internal medicine is often seen as a lack of commitment to surgery.
Most hospitals I am looking to apply are IMG friendly. Which means the surgery and medicine programs are both IMG friendly. Would it be a bad idea to apply to different specialties at the same hospital? I think it would be a bad idea. I suggest you wait and see if you get interviews from the general surgery programs. If you don’t, then there would be no problem applying to internal medicine at the same place. I doubt very much that the two services would talk about any specific applicants. Most surgery programs get hundreds of applications and those applicants who are not offered interviews are not remembered.
Some readers may have other opinions. I hope they will comment.
I did not apply for the 2015 match because I did not have my step 2 CK results until November. It would have been too late. I could have rushed my step 2 but I wanted to get a good score and be a solid applicant. Also I would not have been able to complete my surgical electives in time to get letters of recommendation. At some point, I will be doing research at [a very well-known medical school]. I felt that for these reasons this would make me a better applicant the next year.
Since graduating I have been trying to find a medical related job (scribe) but have had no success. I have reached out to many institutions regarding research opportunities but have come up dry. I may be able to secure a volunteer research position by next month. Do you have any suggestions for me? I knew I would hate being out of the medical field for this long but this was my best bet. Does this gap hurt my chances?
I am concerned that despite your excellent USMLE scores, taking a year off from clinical medicine may cause your application to be rejected immediately. I do not know if a 9 week research elective, even at a premier med school, would be enough to offset your lack of clinical experience over the entire year. Acting as a scribe would not be considered clinical experience.
Another issue is what is the record of your school regarding matching graduates into surgical programs? Since you didn’t tell me your school’s name, I cannot give you any insight into that situation. Even if I did know the school’s name, it may not have published its match results.
To answer your specific questions:
How many gen surg programs should I apply to? I was thinking ~100. That seems reasonable. You should be able to gauge your chances better after you see if you receive any offers for interviews from the 100 programs.
During a gen surg interview, should I be open about my backup specialty? I would advise you to say that you would take a preliminary spot in general surgery if you didn’t match in a categorical position. Admitting that you would do internal medicine is often seen as a lack of commitment to surgery.
Most hospitals I am looking to apply are IMG friendly. Which means the surgery and medicine programs are both IMG friendly. Would it be a bad idea to apply to different specialties at the same hospital? I think it would be a bad idea. I suggest you wait and see if you get interviews from the general surgery programs. If you don’t, then there would be no problem applying to internal medicine at the same place. I doubt very much that the two services would talk about any specific applicants. Most surgery programs get hundreds of applications and those applicants who are not offered interviews are not remembered.
Some readers may have other opinions. I hope they will comment.
Tuesday, August 25, 2015
In 22% of kids with appendicitis, antibiotics do not prevent perforation
Those clambering aboard the "antibiotics for appendicitis" bandwagon should read this interesting paper about appendicitis in children.
A group of emergency physicians from Maimonides Medical Center in Brooklyn, New York found that "Increasing in-hospital time delay from ED presentation to OR appendectomy is associated with increased risk for developing appendicitis perforation in children who present with CT-documented uncomplicated appendicitis."
Children with simple appendicitis who were taken to the operating room longer than 9 hours from the time of ED presentation were much more likely to develop a perforation than those who had surgery in less than 9 hours.
During the four years of the study, 404 consecutive children ≤ 18 years of age had a CT scan diagnosis of acute appendicitis; 156 (38.6%) had evidence of perforation at the time of presentation and were not included in the final analysis.
Monday, August 3, 2015
A high school student has questions about a medical career and pathology vs. surgery
A female high school student asks about pathology, surgery, and medicine in general. [Email edited for length.] See if you agree with my answers.
The field I am most interested in is pathology. I have a very logical mind and would enjoy being able to solve the complex puzzle of disease. I would also like the somewhat flexible hours compared to other more intensive specialties. However, I do have some qualms.
I'm also interested in general surgery. I would love to learn how to perform all the different types of surgeries that surgeons perform. If I were to be a pathologist, would it be "knife-free"? Pathology really intrigues me, but participating in the occasional surgery sounds like it would be extremely interesting and full of learning opportunities.
There is some knife wielding in pathology. Specimens must be properly cut, and there is the occasional autopsy. However, it's definitely not surgery.
What does a pathologist really do? I've looked at various descriptions online, and none of them seem to be very specific. What would a typical day look like for a pathology resident? I was also wondering what types of skills pathologists are taught?
The field I am most interested in is pathology. I have a very logical mind and would enjoy being able to solve the complex puzzle of disease. I would also like the somewhat flexible hours compared to other more intensive specialties. However, I do have some qualms.
I'm also interested in general surgery. I would love to learn how to perform all the different types of surgeries that surgeons perform. If I were to be a pathologist, would it be "knife-free"? Pathology really intrigues me, but participating in the occasional surgery sounds like it would be extremely interesting and full of learning opportunities.
There is some knife wielding in pathology. Specimens must be properly cut, and there is the occasional autopsy. However, it's definitely not surgery.
What does a pathologist really do? I've looked at various descriptions online, and none of them seem to be very specific. What would a typical day look like for a pathology resident? I was also wondering what types of skills pathologists are taught?
Wednesday, November 12, 2014
Can cholecystectomies safely be done at night?
A new study from surgeons at UCLA found that laparoscopic cholecystectomies done at night for acute cholecystitis have a significantly higher rate of conversion to open than those done during daylight hours.
Nighttime cholecystectomies were converted 11% of the time vs. only 6% for daytime operations, p = 0.008, but there was no difference in the rates of complications or hospital lengths of stay.
The study, published online in the American Journal of Surgery, was a retrospective review of 1140 acute cholecystitis patients, 223 of whom underwent surgery at night.
The authors advocate delaying surgery until it can be done in the daytime, but this conclusion needs to be examined.
Although the percentage of gangrenous gallbladders was similar in both groups, it wasn't clear from the data how many patients were semi-elective and how many were true emergencies.
Operative procedure durations were 110.5 minutes for nighttime and 92.4 minutes for daytime cases, and 1.5 and 2.0 days elapsed respectively before the patients were taken to the operating room, both p < 0.0001. The hospital lengths of stay were similar at 3.7 days for the night group and 3.8 days for the day patients. The causes for these lengthy operations, delays in operating, and long hospital stays were not explained in the manuscript.
Nighttime cholecystectomies were converted 11% of the time vs. only 6% for daytime operations, p = 0.008, but there was no difference in the rates of complications or hospital lengths of stay.
The study, published online in the American Journal of Surgery, was a retrospective review of 1140 acute cholecystitis patients, 223 of whom underwent surgery at night.
The authors advocate delaying surgery until it can be done in the daytime, but this conclusion needs to be examined.
Although the percentage of gangrenous gallbladders was similar in both groups, it wasn't clear from the data how many patients were semi-elective and how many were true emergencies.
Operative procedure durations were 110.5 minutes for nighttime and 92.4 minutes for daytime cases, and 1.5 and 2.0 days elapsed respectively before the patients were taken to the operating room, both p < 0.0001. The hospital lengths of stay were similar at 3.7 days for the night group and 3.8 days for the day patients. The causes for these lengthy operations, delays in operating, and long hospital stays were not explained in the manuscript.
Thursday, August 28, 2014
The solo general surgeon is a dying breed. What is next?
This is a guest post by Dr. Paul A. Ruggieri, a general surgeon in Fall River, MA and author of a new book “The Cost of Cutting: A Surgeon Reveals the Truth Behind a Multibillion-Dollar Industry.”
A potential casualty of employment in a hospital system may be the ability to openly disagree with the organization. Will surgeons, as highly paid employees, be confident enough to speak up against hospital policies affecting patient care without worrying about corporate retaliation? Will employed surgeons be able to speak out against hospital cost-cutting measures that infringe on patient care without being labeled whistleblowers or troublemakers? Can they voice their displeasure without worrying about the security of their job? If you are branded “not a team player,” referrals may dry up. Or, you may suddenly be “asked” to take more emergency room call. You may also be asked to travel farther to see patients and generate surgical business in another town. You may be replaced. You could end up as a surgeon without a practice. If let go, you may discover that the clause in your contract prohibiting you from practicing within the area drives you out of town.
Will employed surgeons be able to openly highlight waste and fraud without fear of losing their jobs? As highly paid employees, surgeons risk much if they criticize the organization that employs them, even when the intent is improved patient care. Knowing the economic stakes of speaking against the corporate team, I suspect many may choose to be silent.
A potential casualty of employment in a hospital system may be the ability to openly disagree with the organization. Will surgeons, as highly paid employees, be confident enough to speak up against hospital policies affecting patient care without worrying about corporate retaliation? Will employed surgeons be able to speak out against hospital cost-cutting measures that infringe on patient care without being labeled whistleblowers or troublemakers? Can they voice their displeasure without worrying about the security of their job? If you are branded “not a team player,” referrals may dry up. Or, you may suddenly be “asked” to take more emergency room call. You may also be asked to travel farther to see patients and generate surgical business in another town. You may be replaced. You could end up as a surgeon without a practice. If let go, you may discover that the clause in your contract prohibiting you from practicing within the area drives you out of town.
Will employed surgeons be able to openly highlight waste and fraud without fear of losing their jobs? As highly paid employees, surgeons risk much if they criticize the organization that employs them, even when the intent is improved patient care. Knowing the economic stakes of speaking against the corporate team, I suspect many may choose to be silent.
Friday, May 2, 2014
Antibiotics instead of surgery for appendicitis? I'm still not convinced
Two recent papers have added more fuel to the debate about whether appendicitis can be managed without surgery.
The first paper is a prospective observational study from Italy involving 159 patients over the age of 14 who were thought to have uncomplicated appendicitis. Nonoperative management with oral antibiotics was planned for all of the patients.
Nonoperative management failed within 7 days in 19 (11.9%) patients, all of whom underwent immediate surgery. Appendicitis was found in 17 patients, and 2 had tubo-ovarian abscesses
The abstract says "After 2 years, the overall recurrence rate was 13.8% (22/159)." This is blatantly misleading. The overall recurrence rate was 19 recurrences within 7 days plus 22 more recurrences between 7 days and 2 years for a total of 41 (25.8%) recurrences with 27/159 (17%) of the patients requiring surgery.
If you look at this paper more carefully, you will find the following from Table 3:
Tuesday, December 3, 2013
Surgical training in Brazil
Here is an email I received from a reader in Brazil describing the way surgeons are trained there. You may notice some remarkable similarities and a few differences. My comments are in italics.
After finishing high school, usually at 17 years of
age, to enter med school one must pass the tests. At public universities, the
tuition is entirely funded by the state. These are the most difficult ones to
enter, so the students are generally better. Then there are the private
universities, and they are expensive.
Med school is organized into two years of basics,
two years of clinics and two years of internship (internal medicine, family
medicine, surgery, ob-gyn and pediatrics). Notice—no
college. I also have a feeling that students aren't studying that much
nowadays, but it's also impossible to fail.
Sounds quite familiar. See "Medical
school grading and T-ball: Everyone gets a trophy."
As med school goes on and they meet with the awful
parts of medicine, they tend to focus on quality of life and moneymaking.
Therefore, the most difficult specialties to enter are dermatology, radiology,
anesthesia. Also sounds familiar. Although
some exams are unified, each hospital establishes its own residency exam and
interview. Very different from the US.
General surgery is a two year residency. Different. In the past, general surgery
was more general, but each subspecialty grabbed its cases and now what is
mostly done are cholecystectomy, appendectomy and hernia. Similar in some ways to the US model. So there is another exam to
enter the subspecialty residency: urology, plastic surgery (again, due to
quality of life issues, no inpatients, income, status, the most popular Similar), coloproctology, vascular,
thoracic surgery, surgical oncology, head and neck surgery. Orthopedics,
neurosurgery, ENT don't need general surgery.
I finished general surgery last year, and this year
I've been operating by myself. I've done cholecystectomy, appendectomy,
hernioplasty, Hartmann procedure, skin lesions, abscesses, etc. Of course, at
the beginning, I was not completely confident (which is good in some ways), but
I have had nice results.
I can relate with a lot you posted, your blog makes
me remember residency and my teachers.
I'm out of time now, in the future I'll catch on
some other things. I hope my English isn't too bad, but reading the comments
I've seen that even USA citizens have trouble typing. :D
Of
course, this is just one doctor's perspective, but it's thought-provoking.
What
do you think about the Brazilian system of training surgeons?
Friday, November 8, 2013
Sleep deprivation, surgeons, operations, and outcomes
A new paper found that surgeons who performed elective laparoscopic cholecystectomies after having operated the night before had outcomes similar to those when they were presumably well-rested.
The
retrospective study involved 331 surgeons who did 2078 cholecystectomies after
operating the night before and 8,312 when not operating the night before.
Outcomes both were matched for each surgeon.
Comparing
outcomes after operating
the night before to not found rates of conversion to open - 2.2% vs. 1.9%, risk of
iatrogenic injuries - 0.7% vs. 0.9%, and death - 0.2% vs. 0.1%, respectively.
None of those differences were significant.
The
abstract concluded, "These
findings do not support safety concerns related to surgeons operating the night
before performing elective surgery."
This paper is the latest of
several that show similar results.
So case closed, right?
As
much as I hate to say this, the
paper does not prove that sleep deprived surgeons don't have more complications than
when they are well rested. What it does prove is that conversion rates, not complication rates, are the
same whether the surgeon got adequate sleep the night before or not.
In
the paper, which was published in JAMA, the authors said, "Although not always considered a complication, conversion
to open cholecystectomy may serve as an aggregate end point for many
complications."
I disagree. I know of no previous study confirming that conversion of a laparoscopic cholecystectomy to an open
procedure is a marker for complications. Instead, I believe it is a sign of good
judgment. The sooner a surgeon recognizes that he can't safely do the procedure
laparoscopically, the better off the patient is. A surgeon should never be discouraged
from converting a case to open.
The study probably included enough patients to support its
conclusion that there is no difference in conversion rates, but it is
underpowered to detect a difference in iatrogenic injury rates or mortality
because those events are so infrequent. To conclude that there is no difference
in iatrogenic injury or mortality rates is what is known in statistical circles
as a "Type II error" or failure to reject a false null hypothesis.
The two null hypotheses in this situation were that there is no difference in 1)
iatrogenic injury or 2) mortality rates when surgeons are rested or not.
In other words, the rates of iatrogenic injuries and deaths may not really be different, but the lack of a difference could simply be due to the fact that there were not enough subjects in the study. Iatrogenic injuries and deaths occur so infrequently with laparoscopic cholecystectomy that a study would need a lot more patients in each group to conclude that sleep is not a factor.
In other words, the rates of iatrogenic injuries and deaths may not really be different, but the lack of a difference could simply be due to the fact that there were not enough subjects in the study. Iatrogenic injuries and deaths occur so infrequently with laparoscopic cholecystectomy that a study would need a lot more patients in each group to conclude that sleep is not a factor.
Most media coverage of the paper did not question its
findings. Even Atul Gawande was hooked. Yesterday he tweeted "New @jama
study of daytime surgery by surgeons who operated during night before: found NO
increased complications."
Better studies on the effects of sleep deprivation on
surgeon performance are needed before the issue is settled.
Tuesday, November 5, 2013
Should all surgeons have video assessments of their skills?
Last month, a superb study by the Michigan Bariatric Surgery Collaborative showed that the more skilled surgeons were, the better were their outcomes.
Surgeons submitted a video of their choice depicting their performance of a laparoscopic gastric bypass. Since it was self-selected, it was presumably their best work. At least 10 of their peers, blinded as to the name of the surgeon, rated skills on the video which had been edited to include only the key portions of the case.
Surgeons in the lowest quartile of ratings for surgical skill had significantly more postoperative complications, readmissions, reoperations, and deaths.
A New York Times article about the paper features a couple of short video clips—one from a not-so-skilled and one from a very skilled surgeon. The differences are obvious and dramatic.
According to the discussion section of the paper, the Michigan bariatric surgeons are now watching each other operate and will soon be receiving anonymous feedback about their technique from their peers.
It is not clear whether this will improve the skills of the lower-rated surgeons or have any effect on outcomes.
Many people rightfully praised the research. Some suggested that all surgeons should be scrutinized in this same fashion.
I agree that the study was well-done and shows that technically better surgeons have better outcomes.
But there are some problems with generalizing this to all surgeons.
The American Board of Surgery recently noted that there are almost 30,000 board-certified general surgeons in the US. This raises a number of logistical issues.
Let's say we focus on the most common major surgical procedure—laparoscopic cholecystectomy, 10 surgeon-raters would have to view at least 15 to 20 minutes of video for each of the 30,000 board-certified general surgeons. How long would that take? Who would collect and edit all the videos? Who would make sure that the ratings were consistent? Who would collate and distribute the results? How would follow-up be done? Who would pay for all of this?
And that is just for the board-certified general surgeons. What about the general surgeons who are not board-certified and all the other surgical specialists? Maybe gastroenterologists should have their endoscopy procedures scrutinized. Maybe primary care docs should have selected office visits recorded too.
This is similar to the enthusiasm which surrounded the concept of using retired surgeons to coach other surgeons. The idea was based on the experience of one surgeon, who had access to an expert coach and wrote about it. I blogged about the logistical difficulties that would preclude coaching from becoming widespread. To my knowledge in the two years since I wrote that post, coaching has not caught on as a performance improvement measure.
It's too bad, because in an ideal world, video evaluation of operative procedures and coaching would be great. Unfortunately, we don't live in an ideal world.
Surgeons submitted a video of their choice depicting their performance of a laparoscopic gastric bypass. Since it was self-selected, it was presumably their best work. At least 10 of their peers, blinded as to the name of the surgeon, rated skills on the video which had been edited to include only the key portions of the case.
Surgeons in the lowest quartile of ratings for surgical skill had significantly more postoperative complications, readmissions, reoperations, and deaths.
A New York Times article about the paper features a couple of short video clips—one from a not-so-skilled and one from a very skilled surgeon. The differences are obvious and dramatic.
According to the discussion section of the paper, the Michigan bariatric surgeons are now watching each other operate and will soon be receiving anonymous feedback about their technique from their peers.
It is not clear whether this will improve the skills of the lower-rated surgeons or have any effect on outcomes.
Many people rightfully praised the research. Some suggested that all surgeons should be scrutinized in this same fashion.
I agree that the study was well-done and shows that technically better surgeons have better outcomes.
But there are some problems with generalizing this to all surgeons.
The American Board of Surgery recently noted that there are almost 30,000 board-certified general surgeons in the US. This raises a number of logistical issues.
Let's say we focus on the most common major surgical procedure—laparoscopic cholecystectomy, 10 surgeon-raters would have to view at least 15 to 20 minutes of video for each of the 30,000 board-certified general surgeons. How long would that take? Who would collect and edit all the videos? Who would make sure that the ratings were consistent? Who would collate and distribute the results? How would follow-up be done? Who would pay for all of this?
And that is just for the board-certified general surgeons. What about the general surgeons who are not board-certified and all the other surgical specialists? Maybe gastroenterologists should have their endoscopy procedures scrutinized. Maybe primary care docs should have selected office visits recorded too.
This is similar to the enthusiasm which surrounded the concept of using retired surgeons to coach other surgeons. The idea was based on the experience of one surgeon, who had access to an expert coach and wrote about it. I blogged about the logistical difficulties that would preclude coaching from becoming widespread. To my knowledge in the two years since I wrote that post, coaching has not caught on as a performance improvement measure.
It's too bad, because in an ideal world, video evaluation of operative procedures and coaching would be great. Unfortunately, we don't live in an ideal world.
Subscribe to:
Posts (Atom)