Showing posts with label Pain. Show all posts

Monday, January 8, 2018

Is chronic pain after inguinal hernia repair a big problem?

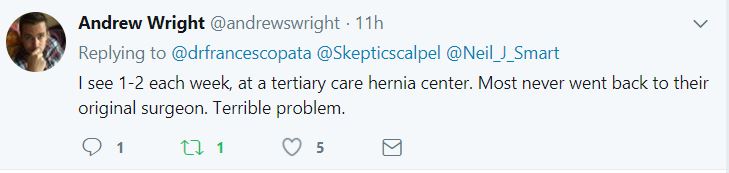
Yesterday one of my twitter followers posted this:
He was referring to a paper in the British Journal of Surgery that said 15.2% of patients who had inguinal herniorrhaphies complained of severe chronic pain one year after the surgery. Open hernia repairs caused significantly more chronic pain than did endoscopic total extraperitoneal [TEP] repairs, but the reoperation rate was significantly higher for TEP procedures.

The study included almost 23,000 patients and was based on data from the Swedish Hernia Registry and a questionnaire sent to the patients one year after their initial hernia operation. Pain was rated on a scale of 1 to 7 and was considered chronic if it was present for more than 3 months and interfered with daily activities.

The recurrence rate for the 18,000 patients who had open anterior mesh repair was 3.4% compared to 23.3% for the 2688 who had TEP repairs.

The authors concluded that the trade-off for less pain was an increased recurrence rate. Only 232 [1.39%] of the 1666 patients with recurrent hernias had undergone repeat herniorrhaphy.

Some of the comments on Twitter were as follows:


When I was in private practice in the early 1980s, I invited all of my post-op hernia patients to return to my office for yearly follow-up at no charge.

One day, a nice elderly gentleman was sitting in the exam room when I walked in. After an exchange of pleasantries, I asked him how his hernia repair was doing. He said he had no problems and was quite happy.

I had him stand up and when he lifted his gown, I saw a softball-sized recurrent hernia. Ever since then, I have not trusted any studies in which follow-up was not done in person.

Based on my experience, the recurrence rate after groin hernia repairs could even be higher than the Swedish study reported.

The incidence of chronic pain after inguinal herniorrhaphy may depend on how surgeons follow their patients.

Thursday, June 1, 2017

The opioid epidemic: What was the Joint Commission's role?

Last year the Joint Commission issued a statement written by its Executive VP for Healthcare Quality Evaluation, Dr. David W. Baker, explaining why it was not to blame for the opioid epidemic. If you haven’t already read it, you should. Here is the first paragraph of that document:

“In the environment of today’s prescription opioid epidemic, everyone is looking for someone to blame. Often, The Joint Commission’s pain standards take that blame. We are encouraging our critics to look at our exact standards, along with the historical context of our standards, to fully understand what our accredited organizations are required to do with regard to pain.”

With the help of an anonymous colleague, I looked at some of the historical context.

In December 2001, the Joint Commission and the National Pharmaceutical Council (founded in 1953 and supported by the nation’s major research-based biopharmaceutical companies) combined to issue a 101-page monograph entitled “Pain: Current understanding of assessment, management, and treatments.”

Here in italics are some excerpts from it. My emphasis is added in bold.

Tuesday, January 17, 2017

More about adhesions and postoperative pain

In November 2016, I wrote about adhesions and whether they are the cause of chronic abdominal pain. I and several surgeons who commented felt they weren't.

Some new information from the February 2017 issue of the journal Surgery is just in. A randomized, double blind, placebo-controlled trial from The Netherlands was originally published in 2003 after one year of follow-up. At that time, there was no apparent benefit from an operation to lyse [divide] all adhesions laparoscopically in 52 patients compared to a placebo operation that involved performing only laparoscopy to assess the extent of adhesions in 48.

The current paper looked at outcomes 12 years after the original surgery was done. Follow-up was available for 73% of the patients—42 in the group who had adhesiolysis and 31 who had laparoscopy only.

The authors concluded, “Laparoscopic adhesiolysis was less beneficial than laparoscopy alone in the long term. Secondly, there appeared to be a powerful, long-lasting placebo effect of laparoscopy. Because adhesiolysis is associated with an increased risk of operative complications, avoiding this treatment may result in less morbidity and health care costs.”

Unfortunately the paper has a few flaws.

Friday, June 12, 2015

Narcotic addicts can sue doctors and pharmacies for "enabling" them

In a 3-2 decision, the Supreme Court of West Virginia ruled that narcotic addicts may sue pharmacies and physicians for facilitating their addictions.

A suit was brought on behalf of 29 pain center patients who had been treated with narcotics for various injuries and became addicted. One article quoted the Chief Justice's explanation: "A plaintiff’s wrongful or immoral conduct does not prohibit them from seeking damages as the result of the actions of others."

The court recognized that most of the plaintiffs "admitted their abuse of controlled substances occurred before they sought help "at the pain clinic.

Another story said, "The justices paved the way for people to claim damages for allegedly causing or contributing to their addictions of controlled substances—even if they broke the law by doctor shopping."

In a dissenting opinion, one justice wrote that the decision “requires hardworking West Virginians to immerse themselves in the sordid details of the parties’ enterprise in an attempt to determine who is the least culpable—a drug addict or his dealer.”

In response to the ruling, the West Virginia Medical Association issued a statement: "It may cause some physicians to curb or stop treating pain altogether for fear of retribution should treatment lead to patient addiction and/or criminal behavior. It may create additional barriers for patients seeking treatment for legitimate chronic pain due to reduced access to physicians. It would allow criminals to potentially profit for their wrongful conduct by taking doctors and pharmacists to court."

A post on the American Pharmacists Association website explained that pharmacists were included in the ruling "because they were aware of the 'pill mill' activities of the medical providers. The plaintiffs said these pharmacies refilled the controlled substances too early, refilled them for excessive periods of time, filled contraindicated controlled substances, and filled 'synergistic' controlled substances."

One newspaper summarized the public reaction to the ruling in an editorial stating, "Those who are illegally abusing prescription narcotics should be prosecuted to the fullest extent of the law. The same goes for medical professionals who are found guilty of committing a criminal act. But telling a drug addict or someone who is illegally abusing prescription narcotics that it is OK to go to court and file what could very well be a frivolous lawsuit is both baffling and shameful. This ruling by the Supreme Court justices is a clear back eye for West Virginia. And it does nothing to help West Virginia’s rampant drug problem."

As I wrote last year, I think the prescription drug abuse epidemic all stems from a 15-year campaign that declared pain is the fifth vital sign—a concept which is both untrue and as we have come to learn, harmful.

I agree with the WVMA. If I were practicing in West Virginia, I would be very reluctant to prescribe narcotic pain medication to any patient.

What do you think?

Friday, August 29, 2014

Pain is not the "5th vital sign"

No, contrary to what you may  have heard, pain is not the 5th vital sign. It's not a sign at all.

Vital signs are the following: heart rate; blood pressure; respiratory rate; temperature.

What do those four signs have in common?

They can be measured.

A sign is defined as something that can be measured. On the other hand, pain is subjective. It can be felt by a patient. Despite efforts to quantify it with numbers and scales using smiley and frown faces, it is highly subjective. Pain is a symptom. Pain is not a vital sign, nor is it a disease.

How did pain come to be known as the 5th vital sign?

The concept originated in the VA hospital system in the late 1990s and became a Joint Commission standard in 2001 because pain was allegedly being undertreated. Hospitals were forced to emphasize the assessment of pain for all patients on every shift with the (mistaken) idea that all pain must be closely monitored and treated .

This is based on the (mistaken) idea that pain medication is capable of rendering patients completely pain free. This has now become an expectation of many patients who are incredulous and disappointed when that expectation is not met.

Talk about unintended consequences. The emphasis on pain, pain, pain has resulted in the following.

Diseases have been discovered that have no signs with pain as the only symptom.

Pain management clinics have sprung up all over the place.

People are dying. In 2010, 16,665 people died from opioid-related overdoses, a four-fold increase from 1999 when only 4,030 such deaths occurred. And the number of opioid prescriptions written has doubled from 109 million in 1998 to 219 million in 2011.

Meanwhile in the 10 years from 2000 to 2010, the population of the US increased by less than 10% from 281 million to 308 million.

Doctors are caught in the middle. If we don't alleviate pain, we are criticized. If we believe what patients tell us—that they are having uncontrolled severe pain—and we prescribe opioids, we can be sanctioned by a state medical board or even arrested and tried.

Some states now have websites where a doctor can search to see if a patient has been "doctor shopping." I once saw a patient with abdominal pain in an emergency room. After looking up her history on the prescription drug website, I noted that she had received 240 Vicodin tablets from various doctors in the four weeks preceding her visit.

That's a lot of Vicodin, not to mention a toxic amount of acetaminophen if she had taken them all herself during that month.

What is the solution to this problem?

I don't know, but as long as pain is touted as the fifth vital sign, I do not see it getting any better.

Wednesday, July 18, 2012

“Damned if you do…”


Here’s a little story from the early days of my first job as a chairman of surgery.

Shortly after I assumed the role of surgical chairman in a community teaching hospital at the ripe old age of 40 and having absolutely no administrative experience, I visited a mentor of mine whom I had known since I was a medical student. He had been serving in a similar role at a larger hospital than mine, and I thought he might be able to share some wisdom about how to be a good chairman.

He was dispensing sound advice for most of the hour or so I spent with him. Then he said something that struck me: Sometimes the unexpected happens and there’s no simple solution. He told me that among the challenges he was facing were two lawsuits.

One was from the family of a patient who had died after a carotid endarterectomy that had been performed by a surgeon in his department. The plaintiffs were suing the hospital and my mentor, the surgical chairman, for allowing what they alleged was an incompetent surgeon to do complex vascular surgery.

The other lawsuit was by a surgeon in his department who had requested privileges to perform carotid surgery, which had been denied by my mentor on the grounds that in his opinion, the surgeon was not adequately trained in carotid surgery.

I never heard the outcome of either case, but it certainly seemed like a no-win situation.

Although that encounter occurred some 25 years ago, the problem persists today. For example, patient advocates are concerned that pain is not being adequately addressed. Yet there is an epidemic of abuse of narcotic prescription drugs that is sweeping all parts of the country.

We also are being criticized for runaway healthcare spending and being encouraged to reduce things like unnecessary testing, while a recent jury verdict for $6.4 million in Philadelphia went against two physicians for failing to order certain tests on a man who had a fatal heart attack 3 months after an emergency department visit for pneumonia.

Some say too many CT scans are being ordered for the work-up of appendicitis with worry that radiation will cause future increased cancer rates. However, in my experience, patients prefer accuracy in diagnosis over a theoretical increased risk of cancer 30 years from now.

Not long ago I was called by an emergency physician who said he had a 17-year-old boy with a textbook case of acute appendicitis. He felt a CT scan was unnecessary. I examined that patient and agreed. I explained to the boy’s mother that I was convinced he had appendicitis and needed surgery. She said, “What about a CT scan?” After a lengthy discussion, I convinced her that the CT scan was not needed. As I made the incision, I said to the OR team, “I sure hope this kid has appendicitis.”

I can think of many more such situations. How should we resolve them?
 
It seems to be the mantra for modern medicine. "Damned if you do and damned if you don't."

Wednesday, July 27, 2011

Bad News For MDs. Researchers Work on Vocabulary for Chronic Pain


Just released on Science Daily is the news that psychiatrists in Buffalo are working on a project to enable chronic pain sufferers to better describe what they are feeling. The docs are using ontology, the branch of metaphysics that studies the nature of existence or being as such. Metaphysics is sometimes called philosophy, especially in its more abstruse branches. [Definitions are from Dictionary.com.]

Here is a quote from the Science Daily article:

"The philosophical definition of ontology is the study of things that exist and how they relate to each other," says [Werner] Ceusters, who also is director of the Ontology Research Group of UB's New York State Center of Excellence in Bioinformatics and Life Sciences. "I am a person and you are a person so we share something. Suppose I drop dead. What lies on the floor? Is that still a person? If it is no longer a person, is it still the very same thing that was sitting here as a person but now is a corpse?"

If you can explain that quote to me, I would certainly appreciate it.

Someone must understand it because the group has received an NIH grant of $793,571 to study the subject.

You may have no idea how many chronic pain sufferers there are. I do. For fibromyalgia [also known as chronic widespread pain syndrome] alone, 17% of a population in a published study from England had it. In my blog on the paper, I pointed out that at the rate people were developing the syndrome, 50% will have it by the year 2033.

Honestly, I do not see standardizing a vocabulary for pain based on ontology leading to anything good.

Thursday, March 24, 2011

Chronic Widespread Pain. Is It an Epidemic?

The term Chronic Widespread Pain Syndrome (CWPS) is synonymous with fibromyalgia (FM). It is characterized by the finding of pain on palpation at 11 or more of 18 specific sites, although the diagnosis of FM apparently can be made with fewer sites involved.

A recent paper, “Road traffic accidents, but not other physically traumatic events, predict the onset of chronic widespread pain: results from the EpiFunD Study,” which was a survey of residents of three different areas in Northwest England, noted some remarkable findings. The publisher was kind enough to provide a full text copy of the paper. Some 17% of 6244 subjects had CWPS at baseline. They were excluded from further study. More than half of the remaining subjects were lost to follow-up. Even more remarkable is that over the four years of the research, 11.6% of the 2069 subjects who did respond to a repeat survey developed CWPS. The authors found that involvement in a traffic accident might lead to an increased incidence of CWPS.

The most remarkable finding was not addressed in the paper. If one does the math for a rate of developing CWPS of 11.6% over four years, one can see by the figure below that at about 22 years from now, half of the study population of 2069 subjects will have developed CWPS. The number of subjects appears on the y-axis and years is on the x-axis. The red arrow at 22 years points to the 1000 subject line.


The authors mentioned some of the limitations of the study in their discussion. The fact that fewer than 50% of those entered into the study were available at its conclusion and the self-reporting of pain and history of trauma were acknowledged as weaknesses.

According to the study's lead author, Dr. Gareth T Jones, whether the subjects with CWPS were being treated with pain medication or being followed by a physician could not be determined. In an email Dr. Jones said, "Individuals with chronic widespread pain are characterized as being high health service users, with multiple tests/investigations, and, yes, medication use (and complementary medicine use) is common."

He agreed that the baseline prevalence of 17% was high but pointed out, "Population studies have fairly consistently shown a prevalence [of chronic pain] of around 12-13%."

Also, there is the matter of potential secondary gain if a traffic accident victim is found to have CWPS. Dr. Jones stated: "Clearly, for people who are reporting a claim then there may be greater financial benefit if that pain is (a) more persistent; and (b) more severe and/or disabling. Of course, that's not to say that the pain isn't genuine. it may be that a long legal process will focus the mind on one's problems, and that this focused attention may genuinely contribute to the exacerbation of symptoms."

When asked about what seems to be a projected epidemic of CWPS in Northwest England Dr. Jones had these comments: "It's not quite as simple as that, but yes I agree, the numbers stack up fairly quickly. People move in and out of different pain states from no pain to regional pain, to widespread pain, to chronic widespread pain and also back in the other direction. Studies have shown, however, that it is rare for someone with chronic widespread pain to no pain at all in a subsequent survey."

What will become of these subjects over the years remains to be seen. Perhaps future studies will help clarify the issues raised.