Showing posts with label Postoperative pain. Show all posts

Monday, January 8, 2018

Is chronic pain after inguinal hernia repair a big problem?

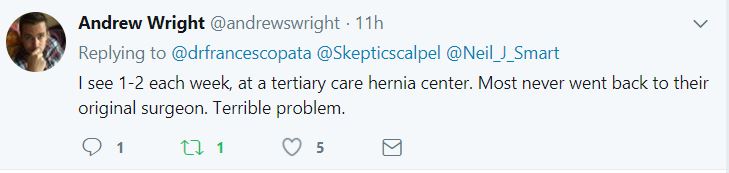
Yesterday one of my twitter followers posted this:
He was referring to a paper in the British Journal of Surgery that said 15.2% of patients who had inguinal herniorrhaphies complained of severe chronic pain one year after the surgery. Open hernia repairs caused significantly more chronic pain than did endoscopic total extraperitoneal [TEP] repairs, but the reoperation rate was significantly higher for TEP procedures.

The study included almost 23,000 patients and was based on data from the Swedish Hernia Registry and a questionnaire sent to the patients one year after their initial hernia operation. Pain was rated on a scale of 1 to 7 and was considered chronic if it was present for more than 3 months and interfered with daily activities.

The recurrence rate for the 18,000 patients who had open anterior mesh repair was 3.4% compared to 23.3% for the 2688 who had TEP repairs.

The authors concluded that the trade-off for less pain was an increased recurrence rate. Only 232 [1.39%] of the 1666 patients with recurrent hernias had undergone repeat herniorrhaphy.

Some of the comments on Twitter were as follows:


When I was in private practice in the early 1980s, I invited all of my post-op hernia patients to return to my office for yearly follow-up at no charge.

One day, a nice elderly gentleman was sitting in the exam room when I walked in. After an exchange of pleasantries, I asked him how his hernia repair was doing. He said he had no problems and was quite happy.

I had him stand up and when he lifted his gown, I saw a softball-sized recurrent hernia. Ever since then, I have not trusted any studies in which follow-up was not done in person.

Based on my experience, the recurrence rate after groin hernia repairs could even be higher than the Swedish study reported.

The incidence of chronic pain after inguinal herniorrhaphy may depend on how surgeons follow their patients.

Thursday, June 1, 2017

The opioid epidemic: What was the Joint Commission's role?

Last year the Joint Commission issued a statement written by its Executive VP for Healthcare Quality Evaluation, Dr. David W. Baker, explaining why it was not to blame for the opioid epidemic. If you haven’t already read it, you should. Here is the first paragraph of that document:

“In the environment of today’s prescription opioid epidemic, everyone is looking for someone to blame. Often, The Joint Commission’s pain standards take that blame. We are encouraging our critics to look at our exact standards, along with the historical context of our standards, to fully understand what our accredited organizations are required to do with regard to pain.”

With the help of an anonymous colleague, I looked at some of the historical context.

In December 2001, the Joint Commission and the National Pharmaceutical Council (founded in 1953 and supported by the nation’s major research-based biopharmaceutical companies) combined to issue a 101-page monograph entitled “Pain: Current understanding of assessment, management, and treatments.”

Here in italics are some excerpts from it. My emphasis is added in bold.

Tuesday, January 17, 2017

More about adhesions and postoperative pain

In November 2016, I wrote about adhesions and whether they are the cause of chronic abdominal pain. I and several surgeons who commented felt they weren't.

Some new information from the February 2017 issue of the journal Surgery is just in. A randomized, double blind, placebo-controlled trial from The Netherlands was originally published in 2003 after one year of follow-up. At that time, there was no apparent benefit from an operation to lyse [divide] all adhesions laparoscopically in 52 patients compared to a placebo operation that involved performing only laparoscopy to assess the extent of adhesions in 48.

The current paper looked at outcomes 12 years after the original surgery was done. Follow-up was available for 73% of the patients—42 in the group who had adhesiolysis and 31 who had laparoscopy only.

The authors concluded, “Laparoscopic adhesiolysis was less beneficial than laparoscopy alone in the long term. Secondly, there appeared to be a powerful, long-lasting placebo effect of laparoscopy. Because adhesiolysis is associated with an increased risk of operative complications, avoiding this treatment may result in less morbidity and health care costs.”

Unfortunately the paper has a few flaws.

Wednesday, November 9, 2016

Do postoperative adhesions cause abdominal pain?

A reader asks whether I think adhesions cause postoperative abdominal pain and if so, how should they be treated?

I have always been skeptical (no surprise) about blaming adhesions for pain.

If adhesions cause abdominal or pelvic pain, what is the mechanism? We know that the intestine can be handled, cut, and cauterized without causing pain. What about tugging or pulling on the bowel? Would that cause pain? I doubt it. How much tugging or pulling can take place within the confines of the peritoneal cavity anyway? A literature search did not turn up any studies on  the mechanism of adhesions causing pain.

UpToDate, the online medical textbook, has a section on this topic. It doesn't address how adhesions cause pain but does discuss the evidence that reoperating on patients with adhesions is not worthwhile.